

The anatomy of the clitoris has implications for women with MS and their partners.
Having a diagnosis of MS and living with MS means having to navigate a complex landscape of sensory changes, numbness, and altered central sensory processing. For many women with MS, this can directly impact sexual function and intimacy. Understanding your own body is a tool to help understand the impact MS has on sexual pleasure.
A newly uploaded anatomical study has completely changed our understanding of the clitoris and its neural pathways. For women with MS and their partners, these new insights into how the clitoris and vulva are wired may offer new possibilities for intimacy, the use of sex aids, and making informed healthcare choices.
Mapping the clitoris in 3D
For a long time, medical illustrations often depicted the clitoral glans (the visible “head” of the clitoris) as having a sparse nerve supply. Because the nerves are largely embedded deep inside the body, standard anatomical dissections struggled to trace them. However, researchers recently used highly advanced, micron-scale 3D imaging technology to map the female pelvis. What they found will rewrite anatomy textbooks:
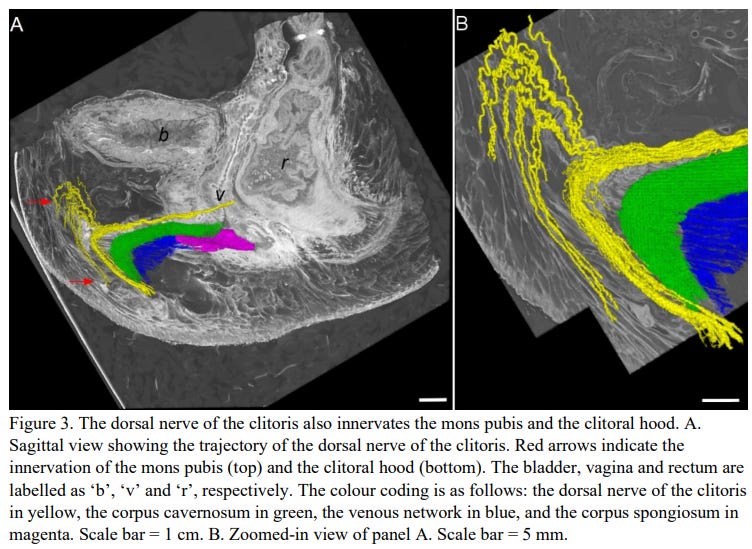
A “Tree-Like” network: The primary sensory nerve—the dorsal nerve of the clitoris (DNC)—does not just gradually diminish as it reaches the glans. Instead, it forms a highly complex, tree-like branching pattern with nerve trunks projecting outward toward the surface. Against the current dogma, this supports what many women know, that the clitoris is well endowed when it comes to sensory nerves and hence sensory inputs. In fact, it may be the most richly endowed sense organ in the female body.
Beyond the glans: The sensory wiring extends much further than previously known. Branches of the dorsal nerve of the clitoris actually travel upward to innervate the clitoral hood and the mons pubis.
Surrounding support: The posterior labial nerve, which is known to supply the labia, was also discovered to innervate the surrounding areas of the clitoral body.
What this may mean for sexual function and MS
Because MS damages the myelin sheath covering the central nerves, you might experience areas of numbness, hypersensitivity, or altered sensation in your genital region. This new anatomical map provides practical information:
Expanding the erogenous map: If the clitoral glans itself is overly sensitive or numb due to MS nerve lesions, you and your partner can broaden your focus beyond the glans. Since we now know that sensory nerve branches extend extensively into the clitoral hood, the mons pubis, and the lateral aspects of the clitoral body, these areas can also be stimulated to achieve sexual pleasure.
Optimising sex aids: Understanding that the nerve network is spread out like a canopy—reaching into the mons pubis and labial structures—means that sex toys and vibrators with wider bases or those designed to lie flat against the vulva can stimulate a much larger cluster of nerve endings than previously thought. You don’t have to rely solely on pinpoint stimulation. It would be an interesting study to survey women with MS and controls to see which sex aids work best in women with MS who have sensory problems affecting the vulva.
Impact on vulvar surgery
If you ever need to undergo gynaecological procedures or elect for vulvar surgeries, this research will allow surgeons to be more careful in how they operate so as not to damage the nerve supply to the clitoris and surrounding erogenous areas. Operations around the vulva, such as labiaplasty, have dramatically increased in popularity. These procedures often involve making incisions in the clitoral hood. Previously, surgeons operated with a defined “danger zone” to avoid nerve damage. However, because this new study proves that sensory nerve branches extend beyond this traditional danger zone into the mons pubis, surgeons will now have to update their techniques to prevent accidental nerve damage and loss of sensation. This comprehensive map is also critically important for reconstructive surgery, such as that performed for survivors of female genital mutilation (FGM) or those having gender reassigment procedures.
The gender gap in anatomical science
I doubt it will shock you to learn that in 2026, we are just now mapping the nerve pathways of the clitoris when we have had this information for the penis for more than 30 years. Why did it take so long? The clitoris has historically been one of the least studied organs in the human body. For centuries, scientific investigation was blocked by cultural taboos surrounding female sexuality. In fact, the clitoris was completely excluded from standard anatomy textbooks until the 20th century, and when it was finally added, it was inaccurately dismissed as just “a small version of the penis”.
While the exact innervation and nerve density of the penile glans have been well-documented for decades, the study of the clitoral glans has heavily lagged behind. This neglect has had real-world consequences for women’s health, leading to surgical risks and a fundamental misunderstanding of female pleasure. By shedding light on the true complexity of the clitoris and its innervation, science is taking an important step forward and addressing the gender imbalance in anatomy research.
For women with MS, this isn’t just anatomical trivia—it can potentially lead to better sexual health, safer medical care, and a deeper connection with your own body.
If you are a woman with MS and have sexual dysfunction due to altered sensation, is the information useful? Do you use sex aids such as vibrators? If yes, is there a particular design that works better than others? Please share this information with others.
Paper
The clitoris is one of the least studied organs of the human body. The detailed anatomy of the clitoris is challenging to address through a gross dissection, as most of its parts are embedded internally, surrounded by pubic bone and several pelvic organs. While clinical imaging methods such as magnetic resonance imaging can capture the gross 3D morphology, they lack the spatial resolution required to resolve the detailed structures. In this study, we generated micron-scale computed tomography images of the female pelvises, leveraging a synchrotron radiation X-ray source. This unique data revealed the complex trajectory of the dorsal nerve of the clitoris, the main sensory nerve of the clitoris. Notably, the nerve trunks within the clitoral glans were revealed, with the maximum diameter ranging from 0.2 to 0.7 mm. They showed a tree-like branching pattern projecting towards the surface of the glans. We also revealed that some branches of the dorsal nerve of the clitoris ramify to innervate the clitoral hood and mons pubis. Finally, the posterior labial nerve, a branch of the perineal nerves, was shown to innervate the surroundings of the clitoris and the labial structures. These findings have an immediate impact on operations performed around the vulva area, such as gender-affirmation surgery andreconstruction surgery after genital mutilation.
Accidental readers
If you have been forwarded this email and are not an MS-Selfie subscriber, please consider subscribing and helping MS-Selfie expand its resources for the broader MS community. MS-Selfie relies on subscriptions to fund its curated MS-Selfie microsite, MS-Selfie books, MS-Selfie Infocards, and other activities that extend beyond the MS-Selfie Substack newsletters.
Subscriptions and donations
MS-Selfie newsletters and access to the MS-Selfie microsite are free. In comparison, off-topic Q&A sessions are restricted to paying subscribers. Subscriptions are being used to run and maintain the MS Selfie microsite and other related activities, as I don’t have time to do this myself. You must be a paying subscriber to ask questions unrelated to the newsletters or podcasts. If you can’t afford to become a paying subscriber, please email a request for a complimentary subscription (ms-selfie@giovannoni.net).
Questions
If you have questions unrelated to the newsletters or podcasts, please email them to ms-selfie@giovannoni.net. Prof. G will try to answer them as quickly as possible.
Important Links
🖋 Medium
General Disclaimer
Please note that the opinions expressed here are those of Professor Giovannoni and do not necessarily reflect the positions of Queen Mary University of London or Barts Health NHS Trust. The advice is intended as general and should not be interpreted as personal clinical advice. If you have problems, please tell your healthcare professional, who will be able to help you.
Email: "The females in my office just asked if you had a female ghost writer."
Thank you for another excellent post, Gavin. It’s disappointing that women’s sexual health has been overlooked for so long. Knowledge truly is power, and understanding our own bodies is vital for comprehensive healthcare. Despite having regular medical care, I’ve never been asked about my sexual health by my GP or neurologist. I hope these essential conversations become a part of routine healthcare.